

 Track Order

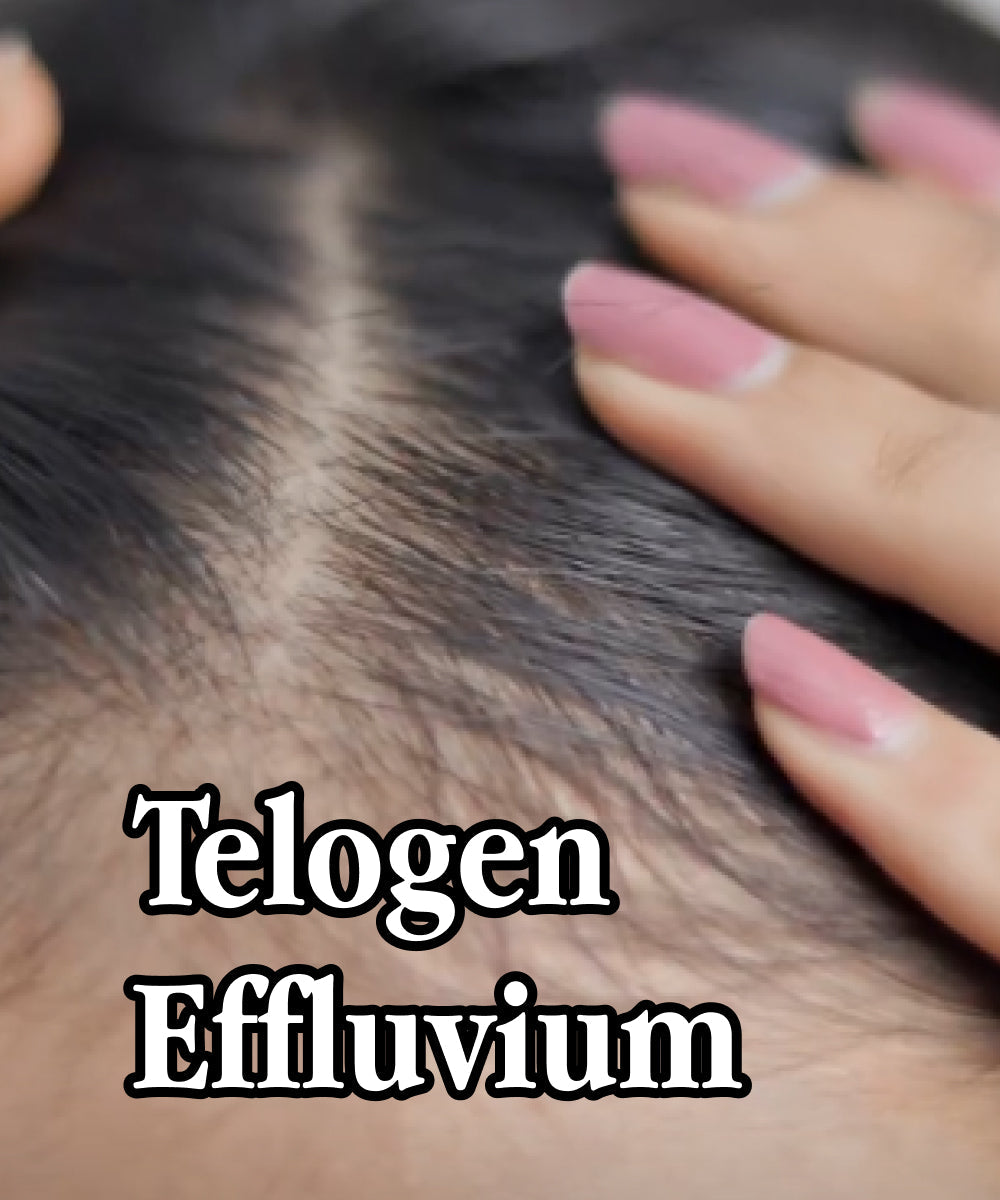
Telogen effluvium is a non-scarring hair loss in which a large number of growing hairs are pushed prematurely into the resting phase by a physical or hormonal stress, then shed together two to three months later. It is the reason hair comes out in handfuls after a fever, a surgery, a pregnancy or a crash diet, and it is fundamentally different from pattern hair loss. Telogen effluvium is diffuse, sudden, traceable to an event, and in its acute form self-limiting. Pattern hair loss is gradual, follows a predictable map on the scalp, and does not reverse on its own.
In a healthy scalp about 85% of hairs are growing and 15% are resting. Under significant stress, roughly 70% of growing hairs can shift into the resting phase at once. Shedding starts an average of three months after the trigger, with a range of one to six months, which is why the cause is almost never the thing that happened last week. Collecting 100 or more shed hairs in 24 hours suggests telogen effluvium. Acute telogen effluvium is self-limiting and recovers once the trigger is corrected, and no topical product has been proven to speed that up.
What is Telogen Effluvium?
Telogen effluvium is a form of non-scarring alopecia characterised by diffuse, often acute, hair shedding, caused by excessive shedding of resting or telogen hair after metabolic stress, hormonal change or medication. Telogen hair is also called club hair, after the shape of its root.
The normal numbers explain the whole condition. According to StatPearls, in a normal healthy scalp about 85% of hair is anagen, meaning actively growing, and 15% is telogen, meaning resting. A hair follicle typically produces anagen hair for almost four years, then rests for about four months. A new anagen hair grows underneath the resting one and pushes it out.
Telogen effluvium is not hair falling out. It is hair that stopped growing months ago finally being evicted. That distinction is why the timing feels wrong to everyone experiencing it.
When the body stays under significant stress, StatPearls reports that approximately 70% of anagen hair can precipitate into the telogen phase.At any time, around 15% of your hairs are resting. After a trigger, far more hairs enter this phase at once. Each one is later pushed out by a new hair growing beneath it, which is why the shedding shows up all together.
How much Hair Fall is Normal, and What Counts as Too Much
There is an actual clinical test for this, and it is one you can run at home.
StatPearls describes the method: collect all shed hair over 24 hours without washing your hair during that period, and repeat the collection weekly for three or four weeks. Collecting 100 or more hairs in 24 hours suggests telogen effluvium.
The repetition matters more than the single result. One heavy day after four days of not washing tells you nothing. Four weekly collections that all come in above 100 tell you something real, and they give a dermatologist something to work with instead of an anecdote.
The other clinical check is the hair pull test. If someone is examined during active shedding, StatPearls notes that a gentle pull removes at least four hairs with each pull. If the acute phase has already passed, the pull test may come back normal, which is a genuine trap: a normal result months later does not mean nothing happened.
Why the Shedding Starts Months after the thing that caused it
This is the single most useful fact in the condition, and almost nobody explains it.
Physiologic stress causes a large number of hairs to abruptly leave the growing phase and enter the resting phase. Growth then ceases for one to six months, on average three months, and during that period nothing visible happens. You do not notice the growth stopping. When those hairs re-enter the growing phase, the strands that had been suspended in telogen are extruded from the follicle, and that is the moment you see shedding.
So the useful clinical question is not "what changed this month". It is what happened to you roughly three months ago. StatPearls puts the causative event at approximately three months before the onset of shedding, with a possible range of one to six months.
Working backwards through a calendar is a more productive first step than buying anything.
Telogen Effluvium vs Pattern Hair Loss: The Four Differences
Androgenetic alopecia, also called pattern hair loss, is a genetically determined disorder caused by an excessive response to androgens, affecting up to 50% of males and females. It is a completely different process from telogen effluvium, and confusing the two is the most common reason people treat the wrong problem for a year.
|
Telogen effluvium |
Androgenetic alopecia |
|
|
Onset |
Sudden, often over days to weeks |
Gradual, progressive after puberty |
|
Distribution |
Diffuse across the whole scalp |
Patterned. In men, vertex and frontotemporal regions. In women, frontal hairline typically spared, diffuse thinning at the crown, often a widening centre parting |
|
Mechanism |
Growing hairs shifted en masse into the resting phase by a stressor |
Androgen receptor activation shortens the anagen phase, causing progressive follicular miniaturisation, driven by elevated dihydrotestosterone and 5 alpha-reductase in balding scalp |
|
Course |
Acute form is self-limiting once the trigger is corrected |
Progressive. Does not reverse without intervention |
There is one important overlap. StatPearls notes that in women, pattern baldness is often unmasked by telogen effluvium, which occurs one to six months after a stressor. In other words, a shedding episode can strip enough density to reveal a pattern that was already developing quietly underneath. If shedding stops but the parting stays wide, that is the likely explanation, and it is a dermatologist's call rather than a shelf decision.
What Actually Causes Telogen Effluvium
StatPearls lists the triggers directly. They fall into four groups.
1. Acute physical stress. Acute febrile illness, severe infection, major surgery and severe trauma. In India this is the category most often missed, because a dengue or typhoid episode in April is not connected to shedding in July by most people, even though the interval is textbook.
2. Hormonal change. Postpartum hormonal changes, particularly a fall in oestrogen, hypothyroidism, and sudden discontinuation of oestrogen-containing medication. Hypothyroidism specifically can lead to chronic telogen effluvium rather than an acute episode.
3. Nutritional deficit. Crash dieting, low protein intake and iron deficiency. StatPearls makes a point about iron worth quoting in substance: because the body prioritises blood over hair, it will shed hair before red blood cell indices become microcytic. Your haemoglobin can read normal while your hair is already responding.
4. Medication and other exposures. The most commonly linked medications are beta-blockers, retinoids including excess vitamin A, anticoagulants, propylthiouracil, carbamazepine and immunisations. Heavy metal ingestion also appears on the list.
Note what is not on that list as a standalone cause: shampoo, hard water, oiling frequency, and most of what Indian hair fall content blames.
How It Is Diagnosed, and the Three Blood Tests Worth Asking About
A detailed history and a thorough physical examination are usually enough to diagnose telogen effluvium. Scalp biopsy is the most useful confirmatory test but, per StatPearls, is seldom necessary if a gentle hair pull produces numerous telogen hairs. Telogen hair is identifiable by a white bulb with no gelatinous sheath.
If a biopsy is done, the histological threshold is specific: if at least 25% but not more than 50% of follicles are in the telogen phase, the diagnosis is confirmed.
The bloodwork is where a lot of Indian shedding gets solved. StatPearls recommends testing for underlying hormonal conditions, chronic metabolic illness and iron deficiency where there is concern:
- Thyroid. A thyrotropin test is warranted when symptoms of hypothyroidism are present, such as tiredness, constipation, weight gain and cold sensitivity.
- Iron. Evaluated with a complete blood count, serum iron, iron saturation and ferritin. Iron saturation is described as the most sensitive indicator of iron deficiency, which is why a normal haemoglobin alone does not close the question.
- Other deficiencies. Where a dietary imbalance such as low iron, zinc or vitamin D is present, hair growth returns after these are corrected.
That last clause is the whole treatment plan in one sentence, and it does not involve a bottle.
Acute Versus Chronic Telogen Effluvium
By definition, shedding in acute telogen effluvium lasts less than six months, and often the shedding period is considerably shorter. A chronic form with a more insidious onset and longer duration also exists.
The distinction changes what you do. Acute telogen effluvium is a self-limited condition: StatPearls states that if the causative event has been identified and appropriately treated, there is no need for further treatment. Chronic telogen effluvium usually means an ongoing driver, most often hypothyroidism or a persistent nutritional deficit, and it needs the driver found rather than the hair treated.
Even in the chronic form, a good cosmetic outcome is expected, even where the shedding continues.
How Long Recovery Takes, and What Nobody Tells You About It
Hair growth may take up to six months to restart, and even longer for that growth to be visible to the person experiencing it. The prognosis for good recovery of hair density in acute telogen effluvium is stated plainly as good. Morbidity is limited to mild cosmetic changes, and there are no reports of mortality.
The gap between "recovery has started" and "recovery is visible" is where most people give up on whatever they were doing and switch to something else, then credit the new thing when the regrowth finally shows. Knowing that gap exists is worth more than any product decision made inside it.
The early signs that regrowth has begun are short, fine hairs standing up along the hairline and parting, which appear before overall density changes. They are easy to mistake for breakage. They are not.
What Products Can and Cannot Do Here
The honest position first, because it is not the one most hair brands take.
No topical product is a treatment for telogen effluvium. Acute telogen effluvium resolves when its cause is corrected. StatPearls is explicit that topical minoxidil has not been proven to promote hair recovery in telogen effluvium, though it has theoretical benefits, and that recent trials support oral minoxidil as an alternative for patients who struggle with topical formulations. If a serum will not do it, a shampoo will not either.
What a product can reasonably do is support the scalp and the hair that is regrowing once the cycle restarts, and avoid adding mechanical stress to a scalp that is already shedding.
Vilvah's Hair Growth Serum at ₹1099 is built around 3% Redensyl, 3% Swiss Alpine Edelweiss extract and Alfalfa callus culture, with Rosemary leaf extract as its first ingredient rather than water, alongside Bhringaraj extract and hydrolysed keratin. It is Minoxidil-free, and Vilvah has filed for a patent on the formulation and tested it on more than 1,000 Indians before launch. It is a growth-phase support product, not a telogen effluvium treatment, and the distinction is the point.
For hair fall where scalp condition and breakage are contributing, Vilvah's Hair Regrowth Oil at ₹625 is the routed product rather than the serum.
Three things matter more than either during an active shedding episode: find the trigger from roughly three months ago, get the thyroid and iron panels done, and stop pulling at hair that is already leaving.
Vilvah, founded in 2017 in Coimbatore by Kruthika Kumaran as India's first milk-based skin and hair care brand, would rather tell you to get a ferritin test than sell you a bottle for a condition that resolves on its own.
Frequently Asked Questions
1. What is telogen effluvium in simple terms?
Telogen effluvium is a temporary, non-scarring hair loss in which a stress event pushes a large number of growing hairs into the resting phase all at once. Those hairs then sit dormant in the follicle for one to six months, averaging three, before being pushed out by new growth underneath, which is the point at which you notice heavy shedding. In a normal scalp about 85% of hair is in the growing phase and 15% is resting. StatPearls reports that under significant stress approximately 70% of growing hair can shift into the resting phase. The shedding is diffuse across the whole scalp rather than patterned, and in its acute form it resolves once the underlying trigger is corrected.
2. How much hair fall per day is normal?
The clinically useful threshold is a 24-hour count rather than a daily impression. StatPearls describes the method: collect every shed hair over a full 24-hour period without washing your hair during that time, then repeat the collection weekly for three or four weeks. Collecting 100 or more hairs in 24 hours suggests telogen effluvium. A single heavy day proves nothing, particularly after several days without washing, because hair that would have shed on each of those days comes out together. Four weekly collections consistently above 100 is meaningful evidence and gives a dermatologist something concrete to assess rather than a description.
3. How do I know if my hair loss is telogen effluvium or pattern baldness?
Four features separate them. Onset: telogen effluvium is sudden, pattern hair loss is gradual and progressive after puberty. Distribution: telogen effluvium is diffuse across the entire scalp, while androgenetic alopecia follows a map, affecting the vertex and frontotemporal regions in men and sparing the frontal hairline in women while thinning the crown and widening the centre parting. Mechanism: telogen effluvium is a mass shift of hairs into the resting phase, whereas androgenetic alopecia is progressive follicular miniaturisation driven by an excessive response to androgens. Course: acute telogen effluvium is self-limiting, pattern hair loss is not. One complication is that the two can occur together. StatPearls notes that in women, pattern baldness is often unmasked by telogen effluvium occurring one to six months after a stressor.
4. What triggers telogen effluvium?
StatPearls lists acute febrile illness, severe infection, major surgery, severe trauma, postpartum hormonal changes particularly a decrease in oestrogen, hypothyroidism, sudden discontinuation of oestrogen-containing medications, crash dieting, low protein intake, heavy metal ingestion and iron deficiency. Medications most commonly linked include beta-blockers, retinoids including excess vitamin A, anticoagulants, propylthiouracil, carbamazepine and immunisations. The critical detail is timing. The trigger typically precedes the shedding by about three months, with a range of one to six months, so the event to look for is not a recent one. For many people in India a viral fever, a dengue episode, a surgery or a rapid weight loss diet from the previous quarter turns out to be the answer.
5. Can iron deficiency cause hair fall even if my haemoglobin is normal?
Yes, and this is one of the more consequential points in the StatPearls entry. Because the body prioritises blood over hair, it will shed hair before red blood cell indices become microcytic, meaning hair loss can precede the changes that show up in a standard haemoglobin reading. StatPearls recommends that iron deficiency be evaluated with a complete blood count, serum iron, iron saturation and ferritin, and identifies iron saturation as the most sensitive indicator of iron deficiency. So a normal haemoglobin result does not rule iron out. If you are shedding and have only had haemoglobin checked, the panel is incomplete. Where a deficiency in iron, zinc or vitamin D is present, StatPearls states that hair growth returns once these factors are corrected.
6. How long does telogen effluvium take to recover?
By definition, shedding in acute telogen effluvium lasts less than six months, and often considerably less. Regrowth is a separate timeline from the end of shedding. StatPearls states that hair growth may take up to six months to restart, and even longer for that growth to be appreciated by the person experiencing it. That gap between biological recovery and visible recovery is where most people conclude that whatever they are doing has failed. The prognosis for good recovery of hair density in acute telogen effluvium is good, and even in the chronic form a good cosmetic outcome is expected. Early regrowth shows as short fine hairs standing up along the hairline and parting, which are frequently mistaken for breakage.
7. Does a hair serum treat telogen effluvium?
No, and any product claiming to is overstating the evidence. Acute telogen effluvium is a self-limited condition, and StatPearls states that if the causative event has been identified and appropriately treated, no further treatment is needed. It also notes specifically that topical minoxidil has not been proven to promote hair recovery in telogen effluvium, though it has theoretical benefits, while recent trials support oral minoxidil as an option for patients who struggle with topical formulations. If the most studied topic in hair loss is unproven for this condition, a cosmetic serum is not a treatment for it either. What a serum can reasonably do is support the scalp and the hair that regrows once the cycle restarts. The productive actions during an active episode are identifying the trigger from roughly three months earlier, getting thyroid and iron panels done, and reducing mechanical stress on the scalp.
Sources
- Hughes EC, Syed HA, Saleh D. Telogen Effluvium. StatPearls, NCBI Bookshelf, updated 1 May 2024. https://www.ncbi.nlm.nih.gov/books/NBK430848/
- Ho CH, Sood T, Zito PM. Androgenetic Alopecia. StatPearls, NCBI Bookshelf, updated 7 January 2024. https://www.ncbi.nlm.nih.gov/books/NBK430924/
Related Stories
-

Lactic Acid for Skin: What It Does That Glycolic Acid Does Not
-

Wheatish Skin Tone: What It Means, and How to Tell If Yours Is One
-

Skincare Ingredients That Underperform on Indian Skin, and What Works Instead
-

Dandruff v/s Dry Scalp: Understand the Real Difference
-

Melanin in Skin: What It Actually Does, and Why Indian Skin Marks So Easily
-

Goat Milk Soap vs Regular Soap: What Actually Changes on Your Skin
-

Fitzpatrick Skin Types: Where Most Indian Skin Actually Sits
-

Skin Tone vs Skin Undertone: Why the Difference Changes What You Buy
-

How to Find Your Skin Undertone at Home: Warm, Cool or Neutral


Leave a comment
All comments are moderated before being published.
This site is protected by hCaptcha and the hCaptcha Privacy Policy and Terms of Service apply.